Who Will Actually Perform Your Cosmetic Procedure?
The consultation, treatment design, procedure itself, and follow-up care may involve different people. What matters is whether medical judgment and responsibility remain connected.
Written by M.D. Bo Won Lee, Director of Springday Clinic Sinchon, Seoul.
Who determines whether the procedure is appropriate for you?
Does the person performing the treatment understand the original plan?
If something looks unusual afterward, who makes the medical decision?
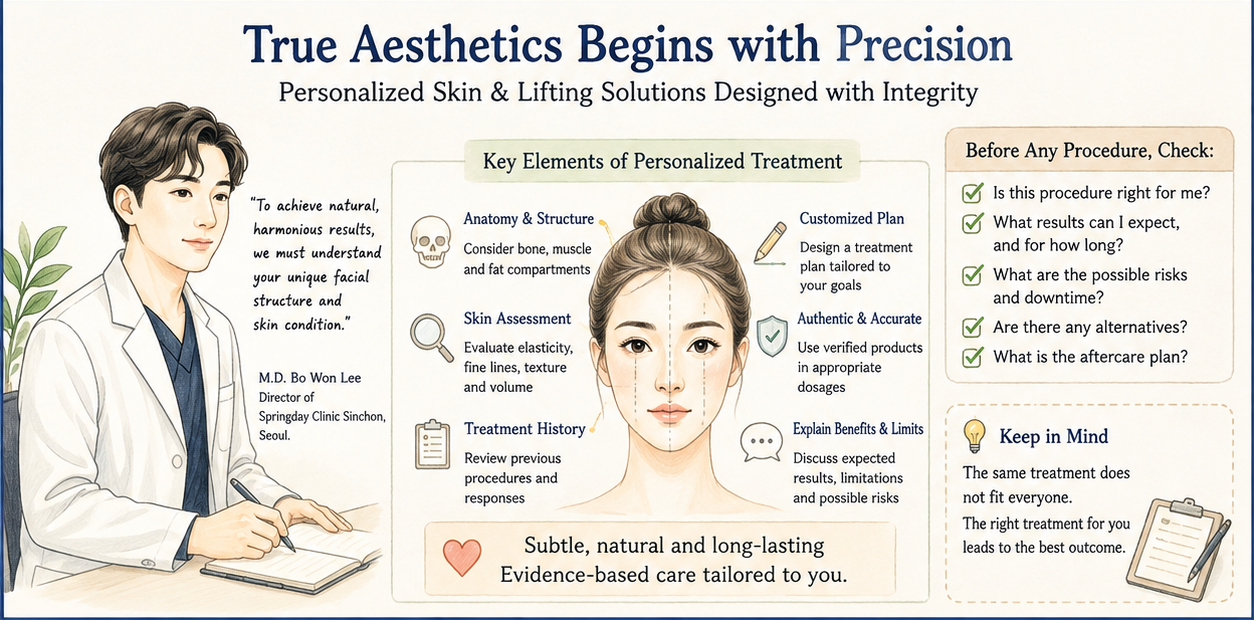
The better question is not simply, “Does the director do it?”
Patients often ask whether the clinic director personally performs a treatment. It is a reasonable question, but it is not the whole story.
A well-run clinic does not require one physician to perform every administrative or preparatory task. Scheduling, standardized photography, basic preparation, routine instructions, and follow-up coordination can often be organized through a consistent clinical system.
What deserves closer attention is the part that requires individual medical judgment.
Who evaluates your anatomy? Who makes the treatment plan? Who actually performs the procedure? And who evaluates you if a complication is suspected?
Four roles may exist within a single treatment journey
The first role is consultation. This may involve gathering your concerns, previous treatments, budget, desired downtime, and expectations.
The second is medical assessment and treatment design. A complaint such as “my nasolabial folds look deeper” does not identify a single anatomical cause. Midface volume loss, skin laxity, skeletal structure, fat redistribution, or the fold itself may contribute in different proportions.
The third role is the procedure itself. The same device or injectable can produce a substantially different treatment depending on location, depth, dose, vector, energy, and distribution.
The fourth is follow-up. Routine swelling and bruising are different from findings that require medical reassessment.
These roles do not necessarily need to belong to one person, but important information should not disappear when responsibility passes from one person to another.
Botulinum toxin: anatomy matters more than a standard injection map
Botulinum toxin is sometimes treated as a highly standardized procedure. In reality, facial muscle mass, contraction patterns, asymmetry, surrounding muscles, and underlying soft and hard tissues can influence treatment planning.
A global consensus on aesthetic botulinum toxin recommends an individualized diagnostic approach, with dose and injection placement based on the target muscles in the context of adjacent muscles and surrounding tissues.
This means that the brand of toxin is only part of the decision. The assessment behind the injection pattern matters as well.
Fillers require both anatomical judgment and a complication plan
Dermal filler treatment involves three-dimensional facial anatomy. Previous fillers, surgery, scarring, tissue thickness, and vascular anatomy can all affect planning.
Hyaluronic acid filler vascular occlusion guidelines emphasize knowledge of facial vascular anatomy, risk assessment by anatomical region, careful observation during injection, and rapid recognition and management of suspected ischemia.
Vascular complications are uncommon, but some can be serious. For that reason, it is reasonable to ask not only who performs the injection but also what happens if an unexpected problem develops afterward.
Energy-based treatments are not defined by the machine alone
The same principle applies to lasers, radiofrequency, and ultrasound-based procedures.
An energy-based treatment is influenced by patient selection, indication, treatment area, device settings, treatment depth, cooling, overlap, and observation of the tissue response.
A 2026 review of laser and energy-based procedure complications describes inappropriate device selection, unsuitable parameters, insufficient patient evaluation, and limited operator experience as relevant contributors to adverse outcomes.
Therefore, comparing device names or shot counts alone does not fully describe the treatment you are receiving.
What can be standardized, and what should remain individualized?
Scheduling
Basic history collection
Standardized photography
General preparation
Routine written aftercare instructions
Follow-up scheduling
Indication and contraindication assessment
Treatment area selection
Dose or parameter decisions
Evaluation of previous procedures
Assessment of asymmetry
Diagnosis and management of suspected complications
The distinction becomes especially important when routine aftercare turns into a medical question. Giving standard advice about expected swelling is not the same as deciding whether unusual swelling represents a complication.
When I would pay particular attention to the actual treating clinician
Does seeing a consultant before a physician automatically mean poor care?
No. Administrative and informational counseling may have a legitimate place in a clinic workflow.
The more important distinction is between providing general information and making a medical decision.
Explaining prices, scheduling, and the usual treatment process is different from determining that a particular injectable, dose, anatomical target, or energy setting is medically appropriate for an individual patient.
In Korea, Article 27 of the Medical Service Act prohibits medical practice by non-medical personnel and medical practice outside the scope of a medical professional's license. Korean case law also evaluates the nature of the act and the degree of physician direction and involvement when distinguishing medical practice and assistance. The legal scope of a specific task cannot be determined from a job title alone and depends on the actual conduct involved.
Questions worth asking before treatment
□ Will the clinician performing my procedure personally assess me first?
□ Will the treatment design discussed during consultation be reviewed again before treatment?
□ Who makes the final decision about injection sites, dose, energy, depth, or shot distribution?
□ Have my previous fillers, threads, lasers, or surgeries been considered?
□ Who should I contact if something looks unusual afterward?
□ Can I be reassessed by a clinician if a complication is suspected?
How we think about treatment at Springday Clinic Sinchon
For facial aesthetic procedures, I believe the device or product should come after the assessment.
Facial skeleton, muscle movement, fat distribution, skin thickness, laxity, asymmetry, previous procedures, and the degree of change a patient actually wants may all affect the treatment plan.
A patient concerned about nasolabial folds may not necessarily need filler placed directly into the fold. A patient asking for jawline slimming may have muscle hypertrophy, fat, skin laxity, skeletal width, or a combination of these factors.
Personalized treatment does not mean doing more procedures. It means deciding what is worth treating, what should be left alone, and how strongly each area should be treated.
FAQ
References
1. Medical Service Act of the Republic of Korea, Article 27.
2. Supreme Court of Korea, Decision 2017Do10007, December 29, 2022.
3. Sundaram H, et al. Global Aesthetics Consensus: Botulinum Toxin Type A—Evidence-Based Review, Emerging Concepts, and Consensus Recommendations for Aesthetic Use, Including Updates on Complications. Plastic and Reconstructive Surgery. 2016.
4. Murray G, et al. Guideline for the Management of Hyaluronic Acid Filler-induced Vascular Occlusion. Journal of Clinical and Aesthetic Dermatology. 2021.
5. Nguyen L, et al. Complications of Laser and Energy-Based Procedures in Dermatology: Classification, Management, and Prevention. Journal der Deutschen Dermatologischen Gesellschaft. 2026.
6. Heydenrych I, et al. Facial aesthetic injections in clinical practice: Pretreatment and posttreatment consensus recommendations to minimise adverse outcomes. 2020.
If you are considering botulinum toxin, fillers, skin boosters, lasers, or lifting procedures in Sinchon, Hongdae, or the surrounding Seoul area, an in-person assessment can help determine which areas may benefit from treatment and which may be better left untreated. Results may vary, and the appropriate approach cannot be determined without evaluating the individual patient.
'Insights' 카테고리의 다른 글
| Why Do Aesthetic Clinics Take Photos Before Treatment? (0) | 2026.08.18 |
|---|---|
| Dermatology Clinic Promotions in Seoul: When Is an Event Price Actually a Good Deal? (0) | 2026.08.17 |
| How Long Should You Take Antibiotics for Acne? (0) | 2026.07.28 |
| Redness, Pigmentation, and Enlarged Pores: Why Treatment Order Matters (0) | 2026.07.27 |
| Why Does Male Beard Laser Hair Removal Hurt So Much? (0) | 2026.07.24 |


